PRP FOR THE HIP
PRP for hip osteoarthritis does not restore cartilage. It changes the joint environment enough to cut pain and improve function, for someone not ready for a replacement. In most reports that lasts months rather than years. First, confirm the hip is the problem. Hip arthritis is groin pain and lost inward (internal) rotation, not pain over the outside of the hip.
People with hip osteoarthritis often place it in the wrong spot. The classic signs are groin pain and a loss of inward (internal) rotation. Pain over the outside of the hip is usually the gluteal tendons. That is a different problem with a different treatment.
Why is the hip harder to treat than the knee?
Three things make this joint less forgiving. It is deep, so an accurate injection needs ultrasound or fluoroscopic (live X-ray) guidance, not landmarks. Its cartilage is thinner than the knee’s and takes higher contact stress. And it moves more predictably to end-stage disease than the knee does. So the decisions come sooner and with less warning.
That last point deserves a spotlight, not a footnote. If your hip is bone-on-bone and your life has shrunk around it, the operation is what changes the structure. Offering an injection series as an equal would be dishonest. But offered for what it actually does at that stage, it is a reasonable thing to want. It buys time and lowers what it takes to get through a day while you decide. And the timing of the operation is yours, not ours. See what the operation actually costs.
What is happening in the joint
As in any osteoarthritic joint, the process is active, not simply erosive. Inflammation of the joint lining (synovium) drives IL-1β and TNF-α. Matrix metalloproteinases (tissue-breaking enzymes) break down the matrix that is left. The bone under the cartilage (subchondral bone) remodels and becomes a pain source. And the capsule thickens and tightens. The stiffness people feel getting up from a chair comes from the capsule as much as the cartilage.
Why some hips deteriorate faster, and how the hip differs from the knee
Built-in structure explains some of it. Femoroacetabular impingement and acetabular dysplasia both load cartilage the wrong way for decades before symptoms appear. Both are worth finding, because they change what should be done.
Beyond structure, the drivers are body-wide, and the hip has its own numbers, not the knee’s. A prospective cohort followed 256,364 people for a median of eleven years. In it, cardiovascular-kidney-metabolic disease at stage 4 carried a hazard ratio of 1.76 (95% CI 1.58 to 1.95) for developing hip osteoarthritis. In people who also carried high genetic risk, it reached 3.10.
Compare that with the knee, where the same study found a hazard ratio of 2.67 rising to 4.00. The metabolic signal is real at the hip and it is smaller than at the knee. We tell you that rather than quote you a knee number for a hip problem. The sex split runs the other way too. Hip risk was greater in men, and knee risk greater in women. It is one more reason the two joints get separate pages here, not one page about arthritis.
A related caution about carrying evidence over: the meta-analysis linking high blood pressure (hypertension) to osteoarthritis found the link at the knee. It did not establish it the same way at the hip. Cited honestly, that is a knee finding. That is why it appears on the knee page and not on this one.
The mechanism, where it does apply, is the familiar one. Inflammation signals from fat tissue (adipose-derived inflammatory signaling) reach the synovium through the blood, no matter the mechanical load. Insulin resistance weakens cartilage cells (chondrocytes), while glycation stiffens collagen. The panel we run is on the metabolic health page.
The social driver here is movement itself, and at the hip it is the main one. Hip pain cuts walking. Less walking worsens metabolic health and weakens the abductors (side hip muscles) that steady the joint. Both feed back into the pain. It is a downward spiral with several entry points, and an injection addresses exactly one of them. That is the case for the abductor work described below, not a case against treatment.
Does PRP work for hip arthritis?
It will not restore cartilage. What it may do is change the inside of the joint enough to cut pain and improve function for a period — months rather than years, in most reports.
Hip trials disagree with each other, and the methods show why. Most never report the platelet dose that reached the joint, many inject without confirming the needle sits inside the capsule, and few pair the injection with rehab or record the metabolic state of the person receiving it. Those are the variables that decide the result, and we control them: a measured platelet dose, image-guided placement inside the hip capsule, and rehab for the glutes, hip stabilizers and gait, alongside work on the metabolic terrain. For someone not ready for arthroplasty (joint replacement), it aims at function in earlier disease and at time and medication burden in advanced disease.
What else causes hip pain besides arthritis?
- Greater trochanteric pain syndrome — lateral (outer) pain, sore to lie on, gluteal tendon rather than joint
- Labral tear and impingement — catching, clicking and groin pain in a younger patient
- Lumbar referral — an L2–L4 back problem sending pain into the groin and thigh, with a normal hip exam
- Sacroiliac joint pain — buttock rather than groin
- Femoral head osteonecrosis (bone death in the ball of the hip) — pain out of proportion with fairly preserved joint space, and a reason for prompt imaging rather than injection
Who is a candidate for PRP in the hip?
The hip is unusual. The first question is not whether you are a candidate. It is whether the joint is the problem at all — and as the list above shows, often it is not. Assume that has been settled: groin pain rather than lateral (outer) pain, limited internal (inward) rotation on exam, and X-ray change that matches what the exam found. Three things then decide.
How much joint space is left. Preserved or moderately narrowed space is treatable. Advanced loss with deformity is not. The hip is the joint where replacement results are most reliably good. If a replacement is what you want, it is the operation that restores the structure. What we will do first is confirm the hip is actually the source, because a large share of pain around a hip is not the joint. Going into that consultation with the pain source identified is worth more than going in with a scan.
Where you are in the timeline. Most people treated here are too young for a replacement to be a sound lifetime decision, or have a medical reason to put one off. That is the situation this treatment exists to address in the hip. It is a fair place to stand.
Whether the muscle around it will be addressed. A hip that is injected and then left to the same weak abductors goes back to the same mechanics. The section below on why the abductors matter is not an afterthought to the injection. It is the half of the treatment that lasts.
Three things rule it out. Suspected osteonecrosis needs an MRI and a different workup, not an injection into a joint whose bone is failing. Lateral (outer) hip pain is usually tendon. It is treated as gluteal tendinopathy, not as arthritis. And imaging that has not been read next to a physical exam is not a diagnosis. It is a picture of a hip that belongs to somebody your age.
How is a PRP hip injection done, and does it hurt?
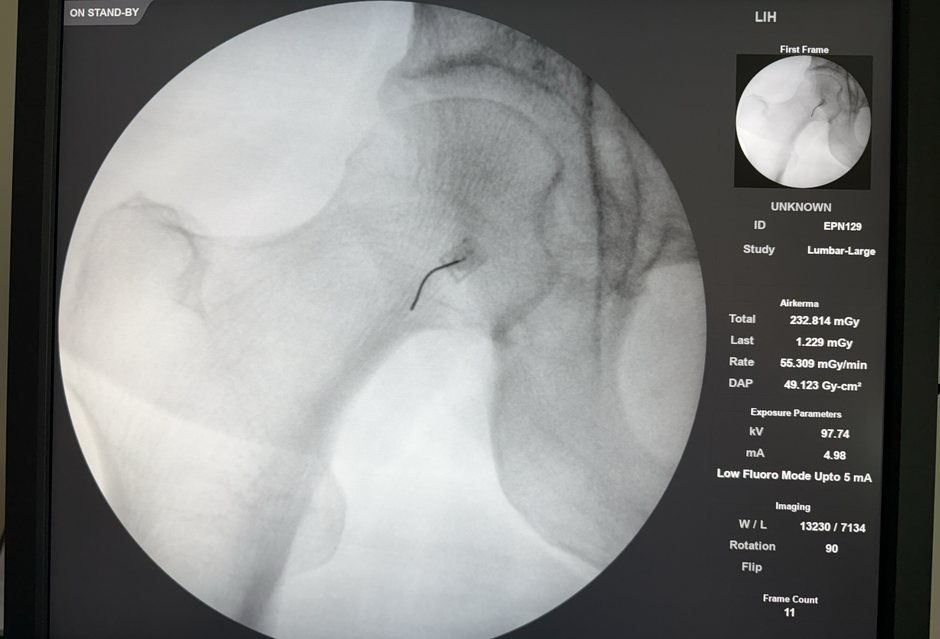
Image-guided, always. A blind hip injection is unreliable, and there is no good reason to try one. Fluoroscopy or ultrasound places the needle inside the joint (intra-articularly). Contrast dye or a direct view confirms it before the preparation goes in.
Some soreness for a few days is normal. A hip flare can be more limiting than a knee flare, simply because you cannot easily take weight off it. Plan for two or three quiet days.
The work that follows
- Weeks 0–2 Walking as tolerated. No loaded deep bending (flexion) or twisting (rotation) at end range.
- Weeks 2–8 Abductor strengthening — gluteus medius and minimus. It lowers joint contact force and is one of the few things that reliably changes hip symptoms.
- Weeks 8–16 Progressive loading, hip hinge mechanics, and gait retraining where a compensating pattern has formed.
- Ongoing Weight and glycemic management, because both act on the cartilage environment, not just the symptom.
What a hip replacement actually costs
The hip is the joint where replacement results are truly good, and nothing below argues for avoiding one. It argues for knowing the ledger before you pick a date.
| What is counted | Reported figure |
|---|---|
| Any in-hospital complication | 27.3% |
| — of which postoperative anemia | 25.2% |
| Still taking opioids at 12 months | 16% |
| Dislocation within 2 years | 3.5% |
| Venous thromboembolism at 30 days | 0.6% |
| Death within 30 days | 0.06–0.23% |
| Lifetime revision risk if replaced at age 46–50 | 27.6% |
| Implant surviving at 10 years | ~94% |
The headline number needs its caveat stated, not buried. 27.3% uses a broad in-hospital definition, and anemia after surgery accounts for most of it. Serious complications are truly uncommon. But “complications are rare” and “the total burden is small” are different claims, and only the first one is true.
The number that changes decisions is the last one. A hip replaced in your forties carries a 27.6% lifetime risk of revision — higher than the knee at the same age. That is what sits under being told you are too young. It is a real limit, not a brush-off. It is also a reason to own the timing rather than hand it over. The full comparison.
What we tell people honestly
Are you putting off a hip replacement out of fear rather than for a clinical reason? That is worth looking at head-on. Fear of an operation is a reason to talk the operation through, not a reason to buy injections instead. The practice gains nothing by keeping you in a chair. Weigh the fear against the actual ledger, not the brochure. The recovery is measured in months. A hip replaced in your forties has a one-in-four lifetime revision risk. A quarter of patients are still in pain a year on. Those numbers argue for making the decision on purpose. They do not argue for making it never, and they do not argue for making it now.
Where PRP fits is earlier, and in a narrower window than the marketing suggests.
Why the abductors matter more than people expect
The gluteus medius and minimus hold the pelvis level when you stand on one leg, which is what walking is. When they weaken, the pelvis drops on the swing side. The body makes up for it by leaning over the standing hip — the Trendelenburg pattern. That lean raises the squeezing force through the joint you are trying to protect.
So abductor weakness is not a result of hip arthritis to deal with later. It is one way hip arthritis speeds itself up, and it is one of the few inputs you can change. A hip that has hurt for two years has almost always lost abductor strength. Restoring it changes joint loading in a way no injection does.
This is the practical reason rehab is not optional here. The injection may cut pain enough to make the strengthening possible. The strengthening is what changes the path. Flip that order — injection as the treatment, exercise as the afterthought — and you get a good six weeks and an unchanged hip.
Where this sits against pain medication
Hip pain is one of the more common routes onto long-term opioids. That is because it hurts at rest and at night, and because people wait years for surgery they have been told they are too young for. The stewardship position is not to withhold anything from someone in that spot. It is to notice that not moving does as much damage as the pain — muscle loss, glycemic drift, broken sleep, isolation. Treatment should aim at restoring movement, not only at covering the feeling.
What people ask before treating a hip
Is PRP as effective in the hip as the knee?
It works when the hip gets what a good knee injection gets: an adequate platelet dose, a needle confirmed inside the joint capsule, and rehab for the muscles that steer the joint. Hip studies look weaker mostly because they skip those steps. PRP for knee osteoarthritis.
My pain is on the outside of my hip. Is this the right page?
Probably not — that is usually gluteal tendinopathy. Gluteal tendinopathy.
Will this let me avoid a hip replacement?
It may put one off in earlier disease. It does not replace one in advanced disease. PRP compared with surgery.
Does it have to be image-guided?
Yes. The hip is too deep for a reliable landmark injection. What to expect.
How soon can I walk after a PRP injection in my hip?
Right away, as tolerated. Plan for two or three quiet days, because a hip flare can be more limiting than a knee flare when you cannot easily take weight off it. For the first two weeks, walk as tolerated but avoid loaded deep bending or twisting at the hip. Abductor strengthening starts around week two.
How long does PRP last in the hip?
Months rather than years, in most reports. PRP does not restore cartilage. It changes the joint environment enough to cut pain and improve function for a period. What makes that window count is the work done during it. Strengthening the gluteus medius and minimus lowers joint contact force. That is the half of the treatment that lasts.
What is the best treatment for severe hip osteoarthritis?
If the hip is bone-on-bone and your life has shrunk around it, a replacement is the treatment that changes the structure. Hip replacement results are reliably good. An injection at that stage can buy time and make days easier while you decide. The timing is yours. A hip replaced in your forties carries a 27.6% lifetime risk of revision.
Is walking good for hip arthritis?
Walking is good for an arthritic hip, and giving it up costs more than the walking does. Cartilage has no blood supply of its own; it is nourished by being compressed and released under load, so a hip that stops moving starves the tissue you are trying to keep. Judge the dose by how the hip feels the next morning, not during the walk, and favor shorter, more frequent walks on level ground over one long one. After a hip injection the rule holds from the first day, because the platelet dose we deliver pays off in a joint that keeps being loaded. What makes a good result hold, and what makes it fade.
Related reading
- Hip, SI joint or lumbar spine?
- Spine and the sacroiliac joint
- Gluteal tendinopathy
- PRP for knee osteoarthritis
- PRP compared with surgery
- Am I a candidate?
For daily hip strength before and after an injection, start with the sit to stand exercise.
Groin or outside — let us work out which
Whether PRP is reasonable for you depends on your tissue, your metabolic health and what you have already tried. That is a conversation, not a form.
12174 Natural Bridge Rd, Suite 303
St. Louis, MO 63044
Sources
- Zhuo Q et al. Metabolic syndrome meets osteoarthritis. Nature reviews. Rheumatology, 2012. PubMed 22907293
- Jones A et al. Importance of placement of intra-articular steroid injections. BMJ (Clinical research ed.), 1993. PubMed 8257889
- Nugent M et al. The lifetime risk of revision following total hip arthroplasty. The bone & joint journal, 2021. PubMed 33641431
- Laigaard J et al. Chronic pain after primary total and medial unicompartmental knee arthroplasty for osteoarthritis: a Danish nationwide cross-sectional survey. Acta orthopedica, 2025. PubMed 41189424
- Tay HP et al. Persistent postoperative opioid use after total hip or knee arthroplasty: A systematic review and meta-analysis. American journal of health-system pharmacy, 2022. PubMed 34537828
- Aggarwal A et al. Epidemiology of total hip arthroplasty: demographics, comorbidities and outcomes. Arthroplasty, 2023. PubMed 36593482
- Hermansen LL et al. “True” Cumulative Incidence of and Risk Factors for Hip Dislocation within 2 Years After Primary Total Hip Arthroplasty Due to Osteoarthritis: A Nationwide Population-Based Study from the Danish Hip Arthroplasty Register. The Journal of bone and joint surgery. American volume, 2021. PubMed 33347013
- Warren JA et al. Have Venous Thromboembolism Rates Decreased in Total Hip and Knee Arthroplasty?. The Journal of arthroplasty, 2020. PubMed 31530463
- Harris IA et al. Declining early mortality after hip and knee arthroplasty. ANZ journal of surgery, 2020. PubMed 31743942
- Bayliss LE et al. The effect of patient age at intervention on risk of implant revision after total replacement of the hip or knee: a population-based cohort study. Lancet, 2017. PubMed 28209371
- Ma Z, Zhang Y, Li L, et al. Association of cardiovascular-kidney-metabolic syndrome with risk of hip/knee osteoarthritis: a prospective cohort study. Maturitas, 2026;212:109056. PubMed 42470749 doi:10.1016/j.maturitas.2026.109056